
Growing up
When a Teen Experiments With or Uses Substances
Write down briefly what is actually known: the teen said they drank alcohol; you saw a particular package; a teacher reported a change in attendance; today the teen is unusually drowsy. Then list what remains unknown. A package does not establish who took what. Lower grades,…
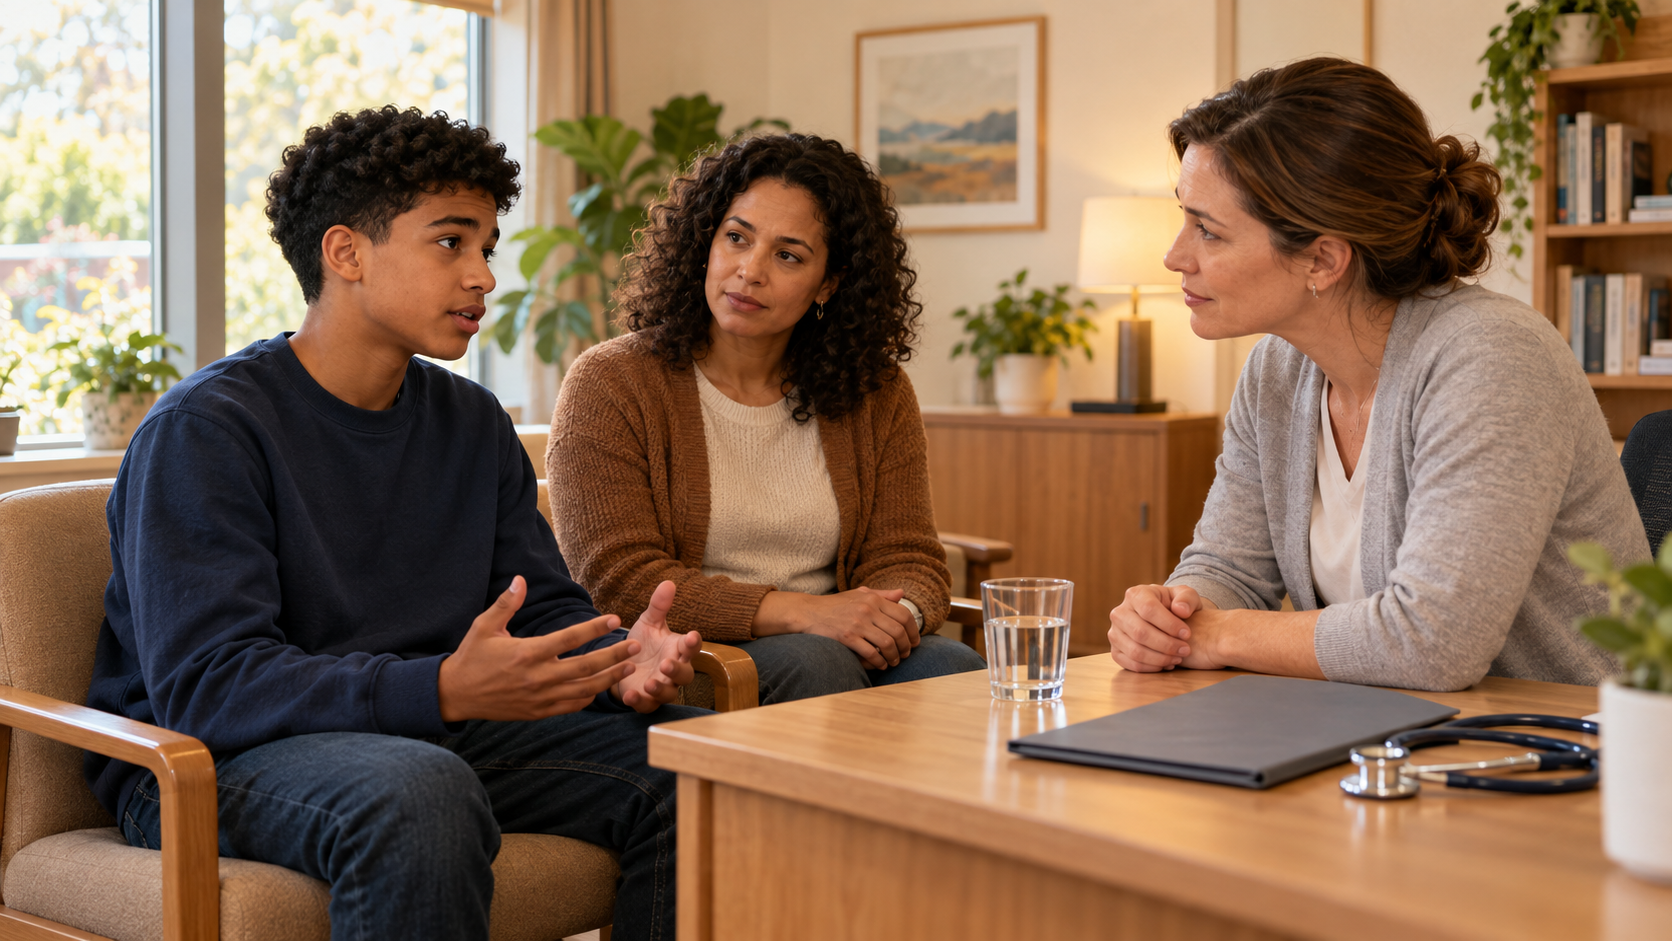
Epigraph
“The heart of the discerning gets knowledge. The ear of the wise seeks knowledge.”
Proverbs18:15, the complete verse in the World English Bible, British Edition. This ancient reflection on attention to knowledge addresses the adult here: an observation should be distinguished from a ready-made conclusion. It demands no confession from a teenager, establishes no diagnosis, and cannot justify delaying medical help for a conversation. Possible poisoning takes the urgent route in sectionII first.
What this article is about. A parent may hear a disclosure, notice a change in behaviour, or find an unfamiliar pill and wonder whether this calls for a conversation today or medical help now. Those are different situations. No single sign establishes substance use or addiction, and a calm conversation cannot replace professional assessment when health may be at risk. This article focuses on what a responsible adult can do: separate known facts from guesses and choose help according to urgency. The teen's age, the substance, any prescribed treatment, and local rules all matter.
I. Separate an observed fact from an assumption
Write down briefly what is actually known: the teen said they drank alcohol; you saw a particular package; a teacher reported a change in attendance; today the teen is unusually drowsy. Then list what remains unknown. A package does not establish who took what. Lower grades, withdrawal from others, or poor sleep can have different causes. Even when use is confirmed, one episode does not let a parent diagnose a disorder or determine the level of risk with a homemade score.
The American Academy of Pediatrics' advice for parents of teens suggests discussing noticeable changes in mood, sleep, appetite, schoolwork, and relationships with a pediatrician. A separate AAP page is specifically about stimulants. It notes that some changes are part of adolescence, while a marked departure from a teen's usual pattern or several changes together may call for attention. Descriptions of stimulants cannot simply be applied to alcohol, cannabis, sedatives, or every other substance. A fact can guide whom to contact and how soon; it cannot replace an assessment.
II. Suspected poisoning calls for medical help first
If there is reason to think the teen swallowed, inhaled, or was exposed to a harmful substance or an unknown pill, contact local emergency medical help immediately. Do not wait for symptoms, a confession, a home test, or the end of a family discussion. Loss of consciousness, difficulty breathing, seizures, or a sudden inability to respond normally make action still more urgent. NHS guidance says poisoning symptoms can appear later; replace the UK numbers and pathways on that page with the ones that actually operate where you are. While help is being arranged, follow your local dispatcher and clinicians rather than informal advice in a chat.
You do not have to prove which substance was taken before you act. Tell clinicians the circumstances you know and show them available packaging, if any. Do not make this teen or another child responsible for getting emergency help for someone else. A responsible adult calls for help, stays with the person who needs it as far as it is safe to do so, and arranges the necessary care of other children. If threats or violence also create immediate danger, a separate safe protection route is needed; a dangerous setting is not the place to negotiate.
III. When conversation is safe, start with what you noticed
If there is no immediate danger, choose a calm time and a place where the teen will not be shamed in public. In your own words you might say: “You seemed different when you came home, and I am worried about your safety. What happened?” Name what you know and allow the teen to correct you. Ask whether help is needed now, and listen. A denial need not erase a fact-based concern; a disclosure need not turn the conversation into an interrogation.
CDC advises adults to discuss substances and mental health with compassion and without judgment, leaving room for further conversations. AAP also recommends talking outside the heat of conflict and returning to the subject rather than expecting one perfect talk. This is communication guidance, not a guarantee of disclosure or an end to use. An adult can state clear safety expectations and family rules; covert home testing, threats of school punishment, and seeking a confession at any cost are not ways to diagnose a disorder. If violence makes a conversation unsafe, do not start it just to follow this advice.
IV. A reason for prompt assessment is not a diagnosis
Contact a pediatrician or another suitable local adolescent-health professional without delay when use is reliably known, happens again, is associated with injury or dangerous behaviour, noticeably disrupts daily life, or accompanies sustained changes in mood, sleep, school, or relationships. Concerns about a pill of uncertain origin, even when you do not know if it was taken, or a teen who reports use but cannot say what they took also merit professional advice. If a harmful exposure may have happened now, use the emergency route above instead of waiting for a routine appointment.
A clinician can evaluate the teen, ask about substances and mental health, and suggest appropriate care; a parent need not label the behaviour “addiction.” AAP explicitly advises involving a pediatrician when notable changes appear, but the changes do not reveal their cause by themselves. Seeking advice remains reasonable after an initial conversation when the concern rests on concrete facts. Do not wait for the teen to adopt your interpretation before asking for an assessment. Ask the local professional how to make contact safely and permissibly for this age and consent situation.
V. Clarify which substance or medicine is involved
Alcohol, nicotine vaping, cannabis, a stimulant, a sedative, and an unknown pill do not produce one uniform picture or call for one identical assessment. Clarify only what is known without coercion: what the teen called it, when the event occurred, whether there is a current prescription, and whether someone else's medicine or a dose different from the prescription may be involved. Do not ask the teen to “prove sobriety” or infer a drug class from their eyes, clothes, or a single mood change.
AAP distinguishes taking a prescribed medicine as directed from nonmedical use, including taking another person's medicine, sharing one's own, or changing a dose without a prescriber's direction. Treatment with a stimulant under clinical supervision does not itself indicate a substance use disorder. If a medicine raises concern, speak with the prescriber or pharmacist; do not stop prescribed treatment at home as a test or punishment. An unknown or counterfeit pill may not contain what it is said to contain. If you suspect a potentially harmful ingestion, use the emergency rule even if the teen looks well for now.
VI. Protect safety in the next ordinary steps
While arranging a talk or consultation, an adult can secure accessible harmful substances and medicines in a way that fits the household, check who is actually responsible for younger children, and plan a safe way home that does not involve riding with an impaired driver. These are actions within an adult's own responsibility, not surveillance of the teen. You can ask another capable, willing adult to actually meet the teen or stay with children. A service appointment does not replace the person who is providing care now.
Do not turn siblings into informants, monitors, or keepers of medicines. Do not ask them to hide threats. If the teen may be under the influence today, the adult's task is to provide a safe place and decide whether medical help is needed, not to stage a public confrontation. AAP also stresses planning a safe ride and letting the teen reach out to an adult; available transport and local circumstances differ.
VII. Find help the teen can actually receive
Start with an actual pediatrician, family doctor, or local adolescent service. Briefly give the teen's age and observed facts; separately explain questions about an unknown substance, medicines, mood, and safety. Ask whether that service sees teens of this age, which language it uses, what it costs, how long the wait is, and where to turn if the situation worsens before the visit. If you are referred elsewhere, confirm that an appointment has been made and the teen can in fact reach the care. A service link, a submitted request, and a completed visit are different things.
An adult can seek advice about their own actions even if the teen is not yet ready to tell everything. CDC describes building a team of support; the parent does not have to solve this alone. The services named on that US page are not automatically available elsewhere. Do not prescribe treatment or stop medication yourself. Keep ordinary connection with the teen and make clear that safety matters more than finding someone to blame, whether or not the teen is ready to talk immediately.
VIII. Clarify privacy limits and use a separate route for violence
Before a visit, ask the actual service how consent, parental involvement, records, portal or billing access, confidentiality limits, and reporting of threats work locally and for the teen's age. Do not promise the teen absolute secrecy or assert that everything must be disclosed to a parent. AAP's US information for teens suggests asking the clinician what can remain private where the teen lives and who can see medical information. It does not set the law outside its jurisdiction. A chance for the teen to speak with a clinician alone may support candour; ask the actual service how that can happen.
If there are threats, coercion, or violence at home, discussing substance use with a dangerous person may raise the risk. NHS describes violence and control in close relationships and a separate way to seek support. Seek a safe local medical or protection contact without requiring a family meeting or confession first. Call for emergency medical help immediately for poisoning or imminent danger. Adults' local duties to protect a child still apply, but neither this UK page nor this article establishes a universal custody or mandatory-reporting rule.
IX. Five optional questions for an adult
These questions organise facts already known; they do not produce a diagnosis. You may answer just one and leave the rest. They are not a prerequisite for an emergency call.
- What did I personally see or hear, and what am I still only assuming?
- Is there reason to suspect poisoning or immediate danger that needs help before any conversation?
- When and with whom could the teen speak safely, without public shame or pressure?
- Which local professional actually sees teens of this age, and has contact with them really happened?
- Which adults will actually provide safety and necessary care until that visit, and which consent and data rules still need checking?
The answers need not be perfect. A new fact can change how urgent the next step is. Necessary help must not depend on the teen's confession, the family's agreement on one explanation, faith, love, or “ideal” motivation.
Key quotation
“I have begun to be a friend to myself.” These are Hecato's words as quoted by Seneca in Moral Letters to Lucilius6.7, Richard M.Gummere's English translation. The letter concerns ethical learning, friendship, and sharing experience, not adolescent substance use or treatment.
The limited connection here is for an adult: acknowledge fear and seek support without using shame to conduct the conversation. Being a friend to oneself can include admitting a limit and asking for help. It does not oblige the teenager to soothe a parent or recover through the right attitude, and promises no end to substance use. Personal support, professional assessment, and urgent medical help have different roles.
Connections between traditions
-
Proverbs18:15 and the CDC's nonjudgmental conversation. Biblical wisdom directs attention towards acquiring knowledge; the modern parent guidance from CDC proposes compassionate listening and continued contact. Their practical overlap is to name a known observation and allow the teenager to correct the adult, as inI/III, rather than extract confirmation of an accusation already decided. Their grounds differ: an ancient ethical verse is not clinical research, while CDC neither interprets that verse nor guarantees honesty or the outcome of one conversation. Listening never means waiting for a confession when poisoning may have occurred: sectionII's medical route has its own urgency.
-
Hecato in Seneca6.7 and adults supporting a teenager. The Stoic statement about friendship with oneself sits within a letter about friends sharing knowledge. Practical sectionsVI/VII concern actual adult and professional help rather than solitary parental heroism. The connection matters when an adult moves from self-blame to checking who can truly help with travel, care, and contact. A fundamental difference remains: mutual friendship in the ancient letter does not equalise adult and child duties. The teenager and siblings do not become observers, medicine keepers, or coordinators of all assistance. Ethical support determines neither a substance's effects, medicine safety, nor local access to records; appropriate professionals and actual conditions retain those roles.
These comparisons clarify listening and support. They claim neither one doctrine across traditions, historical borrowing, nor a spiritual treatment for addiction, and add no prerequisites to necessary help.
Sources and limits
- AAP: How to Talk With Your Teen About Drugs & Alcohol. Pediatrician's parent advice, updated 12 November 2025; not a diagnostic scale or a guarantee of a conversation's outcome.
- AAP: Stimulants and Teens. Parent explainer about a specific drug class, updated 28 July 2026; stimulant descriptions cannot be applied to every substance.
- CDC Free Mind: Talk To Your Teen. US public-information page about communication, reviewed 27 March 2026; its named services are US-specific.
- NHS: Poisoning. UK medical information, reviewed 12 June 2025; suspected poisoning calls for immediate medical advice, while the local emergency number may differ.
- AAP: Dangers of Prescription Drug Misuse. Parent advice, updated 18 November 2024; distinguishes treatment from nonmedical use, and US legal claims do not apply everywhere.
- AAP: Privacy in Health Care: Information for Teens. US advice for teens, updated 11 February 2026; confidentiality and consent must be checked with the actual local service.
- NHS: Domestic violence and abuse. UK protection information, reviewed 23 June 2026; local protection routes and duties may differ.
The examples and order of questions are original editorial guidance. The sources do not establish a diagnosis, legal rule, or outcome for an individual teen. This article does not replace emergency care or an individual medical assessment.
- Proverbs18, WEB British Edition — full chapter and public-domain notice read24October2026; complete verse18:15, English translation rather than the Hebrew original.
- Seneca, Moral Letters6 — full letter read;6.7 quotes Hecato. Richard M.Gummere translation; collection title1918/1925 checked. The complete sentence is used, not medical evidence.
Tags
teenagers; substance use; parents; conversation; professional assessment; safety; poisoning; medicines; confidentiality; violence; help; family.
About the authors
Andrey Zarinsh — author and founder of United Wisdom. He explores inner transformation, the unity of traditions, intercultural dialogue, and contemporary spiritual discipline. Instagram: @andrey.zarinsh.
Maria Evilkut — co-author of United Wisdom. Alongside her research, she seeks to test these ideas in practice and observe how principles of unity and mutual understanding work in real life between people and cultures. Instagram: @ilkutki.
Content date
15 October 2026. English version.